

Understanding PCOS (Now PMOS) and How It Affects Fertility
"You've got PCOS."
It's a phrase many patients hear in fertility clinics—but often without a clear explanation of what it means, what to expect, or what comes next.
Polycystic Ovary Syndrome (PCOS) is the most common endocrine disorder among women of reproductive age, affecting approximately 1 in 8 to 1 in 10 individuals. Despite being so widespread, it remains one of the most complex and misunderstood conditions in reproductive health.
At Indiana Fertility Institute (IFI), we're here to break it down and support you every step of the way.
PCOS Has a New Name: PMOS
You may have recently seen this condition referred to as PMOS—polyendocrine metabolic ovarian syndrome. In May 2026, a global consensus of more than 50 patient and professional organizations, published in The Lancet, formally renamed PCOS to PMOS.
The reason is simple: the old name was misleading. "Polycystic ovary syndrome" suggests the problem is ovarian cysts—but as we'll explain below, those aren't true cysts, and the ovaries are only one part of a much bigger picture. The new name reflects what the condition really involves: multiple hormone systems (polyendocrine) and a strong metabolic component, alongside its effects on the ovaries.
Two things to know if you've already been diagnosed:
-
Nothing about your diagnosis or treatment changes. The way PCOS/PMOS is diagnosed and treated is exactly the same. The name is more accurate; the medicine is unchanged.
-
You'll see both terms for a while. Because "PCOS" has been used for decades, you'll continue to see both names during the transition. We use PCOS/PMOS throughout this article so it's clear they refer to the same condition.
What is PCOS/PMOS?
PCOS/PMOS is a condition characterized by a combination of hormonal imbalances, irregular ovulation, and often, polycystic-appearing ovaries.
Unlike a disease that has a single known cause, a syndrome is defined as a group of symptoms that consistently occur together. That's why it can look very different from person to person. Some patients have obvious symptoms, while others may only discover they have PCOS/PMOS when they're trying to conceive.
It can present differently based on age, body type, and reproductive stage. For example:
-
An adolescent may struggle with acne and irregular periods.
-
A lean adult may have subtle hormone imbalances.
-
An overweight patient may experience multiple metabolic symptoms.
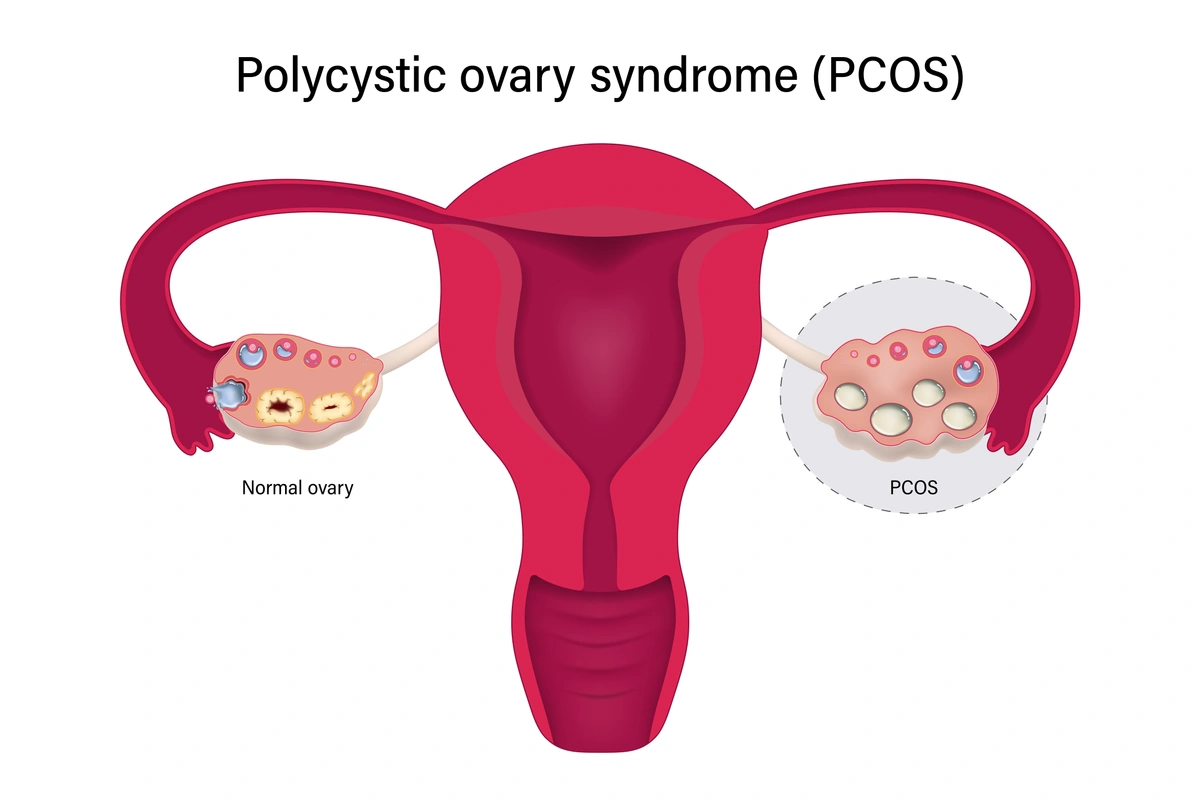
Illustration of a “normal” ovary and one with PMOS/PCOS
How is PCOS/PMOS Diagnosed?
Because it's so variable, several medical organizations have proposed different—but similar—criteria for diagnosis over the past two decades. This has not changed with the new name. Most clinicians agree that a diagnosis requires two of the following three features:
1. Elevated Testosterone Levels (Hyperandrogenism)
Patients often produce higher-than-average levels of androgens (including testosterone). These aren't "male-level" hormone amounts, but they can cause symptoms like:
-
Excess facial or body hair (hirsutism)
-
Acne
-
Hair thinning on the scalp
High testosterone levels also interfere with ovulation, making it harder to conceive.
2. Irregular or Absent Menstrual Periods
At least 80% of individuals with PCOS/PMOS experience irregular cycles. This is often due to anovulation (not releasing an egg), which significantly impacts fertility.
When left untreated, infrequent periods can also increase the risk of endometrial hyperplasia, a condition where the uterine lining becomes too thick, and, over time, endometrial cancer. That's why it's important not to go more than three months without a full menstrual bleed—even when pregnancy isn't the goal.
3. Polycystic Ovaries on Ultrasound
Despite the name, "polycystic ovaries" are not actually filled with cysts. What we see on ultrasound are many small immature follicles arranged around the edges of the ovary, giving it a "string of pearls" appearance. These ovaries are often slightly enlarged and may not release eggs properly without medical support.
This misunderstanding is exactly why the condition was renamed: the "cysts" that gave PCOS its name were never really cysts at all, and focusing on them obscured the hormonal and metabolic issues that matter most.
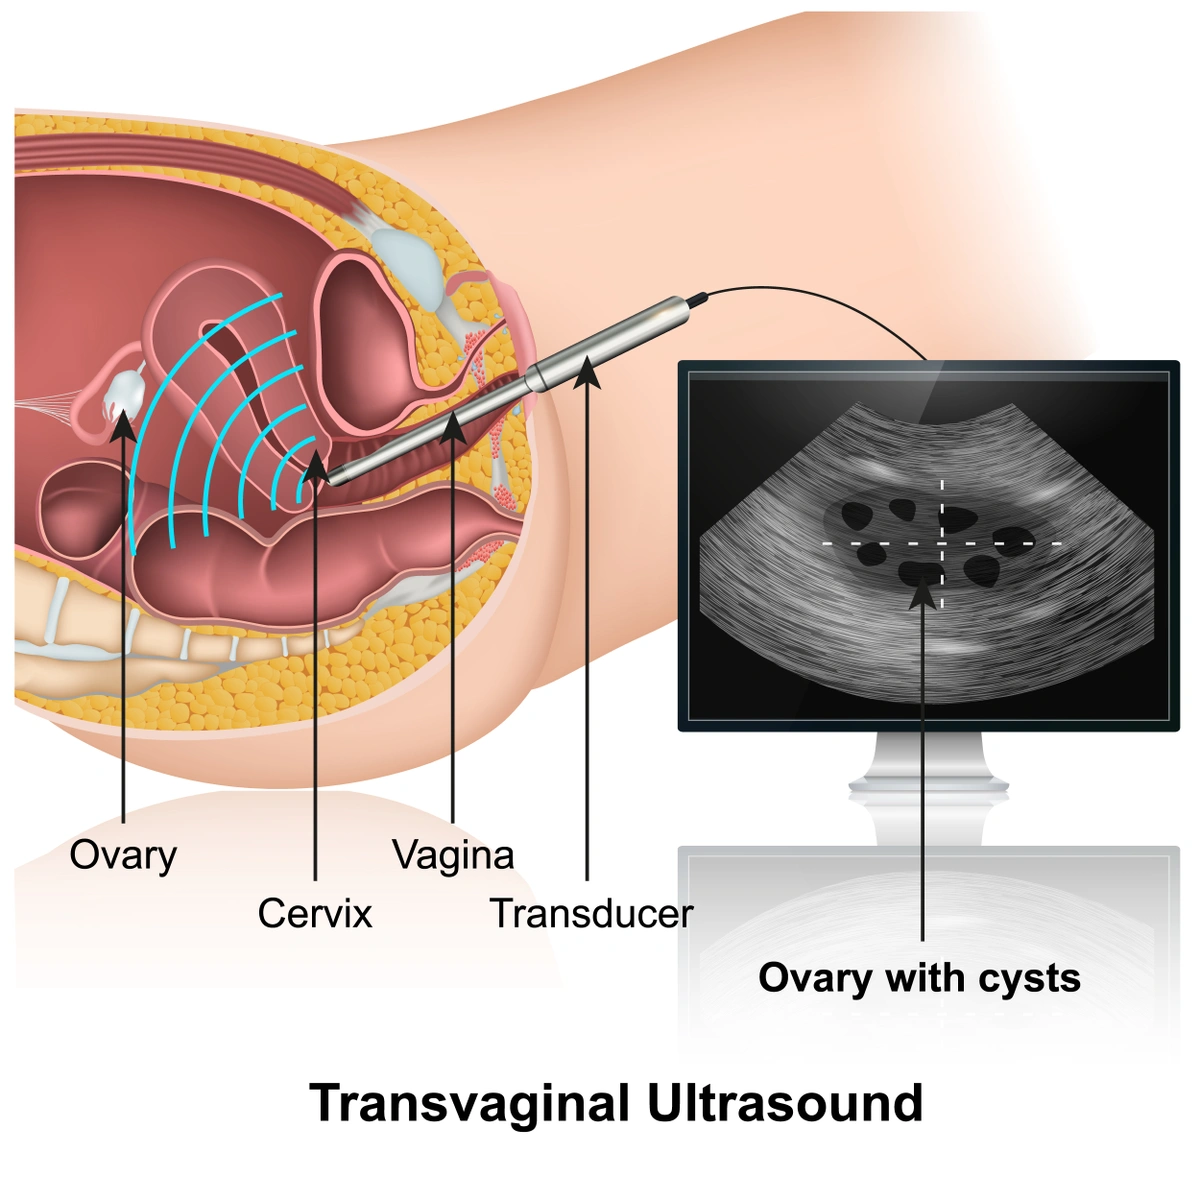
Illustration of a transvaginal ultrasound of an ovary with "cysts" (which are really immature follicles)
The Link Between PCOS/PMOS and Insulin Resistance
One of the key drivers behind the condition is insulin resistance. This means the body doesn't respond effectively to insulin, leading to elevated blood sugar and insulin levels. Over time, this can increase the risk of:
-
Type 2 diabetes
-
High cholesterol
-
Weight gain
-
Cardiovascular disease
This metabolic dimension is so central to the condition that it's now part of its name—the "metabolic" in polyendocrine metabolic ovarian syndrome. It's also why lifestyle changes—like balanced nutrition, regular exercise, and weight management—are essential parts of care, even for patients who are not currently trying to conceive.
How PCOS/PMOS Affects Fertility — And How IFI Can Help
PCOS/PMOS is one of the most common causes of ovulatory infertility—but the good news is that it's also one of the most treatable. Because the core issue is often irregular or absent ovulation, restoring regular ovulation is frequently enough to help many patients conceive.
At IFI, we offer a range of evidence-based fertility treatments tailored to the unique needs of patients with PCOS/PMOS, including:
-
Ovulation induction using medications like letrozole or clomiphene
-
In vitro fertilization (IVF) for more complex cases
-
Metformin therapy, in some cases, to support insulin regulation and ovulation
Finding the right medication and dose can take time and fine-tuning, but we're with you every step of the way to optimize your response and support your goals. A fertility evaluation helps us understand your specific hormone and ovulation patterns so treatment can be tailored to you.
Managing PCOS/PMOS Beyond Fertility
Even when you're not actively trying to conceive, managing the condition is important for your long-term health. Treatment options may include:
-
Hormonal birth control to regulate menstrual cycles and reduce androgen symptoms
-
Lifestyle support for weight management and insulin sensitivity
-
Regular screenings for diabetes and cardiovascular risk factors
When to See a Specialist
If you're experiencing irregular cycles, unwanted hair growth, persistent acne, or difficulty getting pregnant, it's a good idea to schedule a visit with a Reproductive Endocrinologist.
At Indiana Fertility Institute, our team specializes in helping patients with PCOS/PMOS navigate diagnosis, treatment, and fertility planning with compassion and clarity.
Frequently Asked Questions
Is PCOS the same as PMOS? Yes. PMOS (polyendocrine metabolic ovarian syndrome) is simply the new, more accurate name for the condition long known as PCOS (polycystic ovary syndrome). They refer to the same condition, and you'll see both terms used during the transition.
Does the new name change how PCOS/PMOS is diagnosed or treated? No. The rename, finalized through a 2026 global consensus, updates the terminology only. Diagnosis still relies on the same "two of three" criteria, and treatment options are unchanged.
Why was PCOS renamed? The old name implied the condition is caused by ovarian cysts. In reality, the "cysts" seen on ultrasound are immature follicles, not true cysts, and the condition involves multiple hormone systems and metabolism—not just the ovaries. The new name reflects that fuller picture and aims to reduce diagnostic delays.
Can I still get pregnant if I have PCOS/PMOS? For many people, yes. PCOS/PMOS is one of the most common—and most treatable—causes of ovulatory infertility. Treatments that restore regular ovulation, such as ovulation-induction medications, help many patients conceive, and additional options like IUI and IVF are available for more complex cases.
What's the first step if I think I have PCOS/PMOS? Schedule an evaluation with a reproductive endocrinologist. A visit can confirm the diagnosis, screen for related metabolic risks, and map out a treatment plan tailored to your goals—whether or not you're currently trying to conceive.
The Bottom Line
Whether you know it as PCOS or its new name, PMOS, this is a common, complex, and highly manageable condition—and a diagnosis is the beginning of a plan, not a dead end. With the right evaluation and an individualized treatment approach, most patients have real, effective options for both their fertility and their long-term health.
You're not alone—and PCOS/PMOS doesn't have to define your future. If you're ready to better understand your symptoms or explore your fertility options, request a consultation with the team at Indiana Fertility Institute.